The most revealing thing Komodo Health ever found may not have been a disease trend. It was a doctor who was famous on paper and absent in practice. Medical-affairs teams had long identified key opinion leaders by counting publications and clinical-trial appearances. Komodo added another signal: actual clinical activity. Some names still treated large patient panels. Others, co-founder Web Sun later recalled, had not seen a patient in 12, 24 or even 36 months.
That small discovery contains the whole company. Healthcare has plenty of data, but its pieces often arrive late, live in separate systems and answer yesterday's question. Komodo's wager was to assemble those pieces into a longitudinal view of how de-identified patients move through doctors, hospitals, pharmacies, laboratories and insurers - then put software on top that makes the view useful.
The result is the Healthcare Map, which Komodo says now contains more than one trillion linked records representing more than 330 million de-identified patient journeys. The company sells access and applications to drugmakers, providers, payers, researchers, patient advocates and, through a 2025 Nasdaq partnership, financial firms. It does not treat patients. It sells the intelligence used by people deciding where to run a trial, how to measure an outcome, which care gap to attack or how a therapy is performing.
The expensive part came before the clever part
Arif Nathoo, a physician and former McKinsey partner, and Web Sun, a life-sciences strategist, founded Komodo in 2014. They had watched large healthcare companies repeat the same unhappy ritual: buy data from several vendors, spend months cleaning and joining it, hire consultants to run an analysis, then repeat the exercise when the answer went stale. In a 2024 interview, Sun said life-sciences teams commonly worked with four data vendors and spent seven months preparing before analysis began.
The founders chose a “full-stack” answer. Komodo would acquire and link data, build the cleansing and entity-resolution machinery, and create the applications used at the end. This was not a cheap contrarian gesture. Sun said millions, then tens of millions of dollars, went into the Healthcare Map. The software had to normalize records, remove duplicates, protect identity and decide when entries from different sources belonged to the same person - all before a user asked a question.
Aperture was the first proof that this machinery could become a product. It gave medical-affairs teams a richer way to find influential clinicians and promising trial sites. Instead of another static consulting deck, it could update as the underlying clinical picture changed.
“Traditional KOL consulting projects can cost anywhere from $150,000 to $450,000 per year.”Web Sun, co-founder, describing the alternative workflow
Komodo does not publish list prices, so there is no honest sticker price to print for its software. The useful cost comparison is the work it seeks to replace. Sun put traditional annual KOL studies at roughly $150,000 to $450,000, often rerun 18 to 24 months later. He also described a typical analysis worth about $400,000 being delivered inside MapView. Those are vendor claims about customer value, not a public rate card.
The map worked. The customers barely used it.
The first thing that failed was not data collection. It was utilization. After Komodo had poured tens of millions into the Map, Sun said medical teams were running only a limited set of analyses. They were not routinely using it for deeper commercial analytics or longitudinal outcomes research. The grand platform risked becoming an expensive library whose patrons checked out the same three books.
That changed the product strategy. Rather than assume every buyer would invent its own use cases, Komodo packaged recurring questions into applications. Prism helped teams define patient cohorts. Sentinel supported custom algorithms and linked analysis. Pulse generated clinical alerts. MapView supplied pre-built dashboards. MapExplorer let non-coders examine diseases, therapies and patient populations. MapLab Enterprise put business users and data scientists in one governed environment.
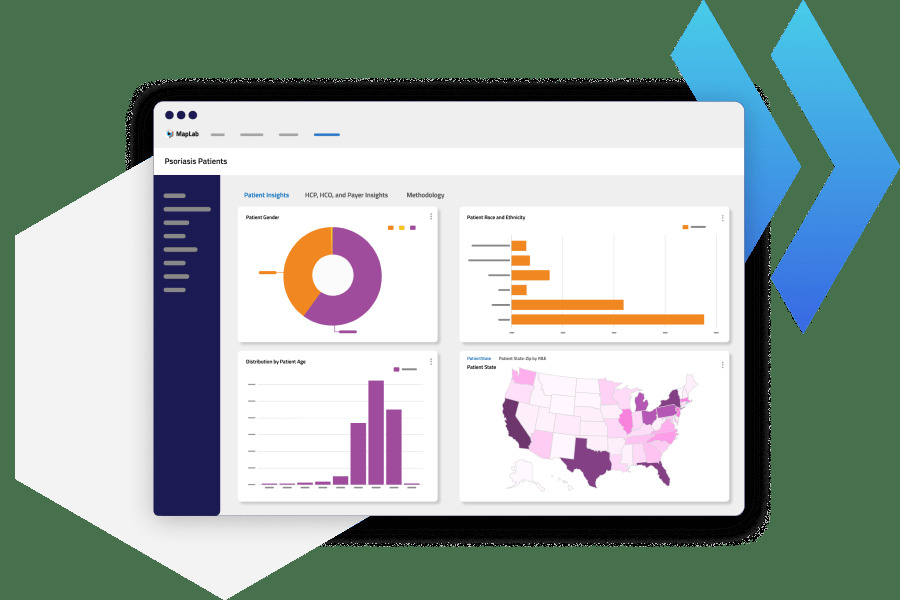
The products address different jobs, but the business model rhymes across them: enterprise subscriptions, data access, specialty datasets, software workflows and services. The 2021 acquisition of Salesforce specialist Mavens added enterprise applications for medical information, publications, patient engagement and commercialization. Breakaway Partners added market-access expertise. Komodo was moving outward from a data foundation into the daily operating systems around a therapy.
Marmot is an audit trail wearing a chat box
Generative AI gave Komodo a new interface for an old ambition. MapAI first let users create cohorts and ask early questions in plain language. Marmot, launched in August 2025, became the broader intelligence layer. It routes subtasks to models, draws on healthcare-specific analytical methods and returns code and source trails intended to make results reproducible.
This distinction matters. A pharmaceutical analyst cannot take “the chatbot seemed confident” into a regulatory review. The analysis needs a defined population, defensible methodology, versioned intermediate steps and a result another analyst can rerun. Komodo's pitch is therefore less magical than most AI marketing - and more practical. The system should show its work.
The earliest customer stories are promising but should be read as examples, not controlled trials. Novo Nordisk executive Christopher Blanchette said work that once took six months had, at its shortest, been completed over a weekend. NCQA reported that quantitative testing of a new quality measure, historically a two-to-three-month process, took about a month for three insured populations using Komodo. Alnylam said reporting cycles moved from months to hours as it built custom Marmot agents; in June 2026 it expanded the deployment beyond its initial commercial team.
Those cases show what people can do with the platform: explore a patient population, design a cohort, compare treatment paths, locate potential trial sites, find care gaps, profile providers, measure utilization or monitor a market. ZERO Prostate Cancer is using Komodo to identify screening breakdowns affecting Black men, veterans and underserved rural communities. Nasdaq distributes de-identified medical-claims insights to investors. The same map supports very different decisions because the application layer narrows the job.
A crowded market, and a moat with conditions
Komodo sits between several categories that already contain formidable companies. IQVIA sells data and services to life sciences. Optum owns payer-adjacent data advantages. Datavant specializes in linking health records. Truveta aggregates health-system data. Flatiron is deep in oncology. HealthVerity and TriNetX address identity, evidence and research workflows. Epic and Oracle Health can move from the electronic-record layer outward. A determined pharmaceutical company can also build internally or keep hiring consultants.
Komodo's answer is integration: a wide longitudinal dataset, analysis-ready infrastructure, healthcare applications and AI in one stack. That can reduce vendor handoffs and keep definitions consistent across teams. It can also create dependence on one provider. The company's advantage holds only if its underlying sources remain broad, current, affordable and linkable - and if its methods stay visible enough to challenge.
The privacy bargain also shapes the product. Komodo says personally identifiable information is not shared and that records are de-identified. That protection is essential, but it limits some forms of direct follow-up. Real-world data can reveal patterns; it does not automatically explain causation. Bias in who appears, how something is coded and which sources are available can survive even excellent engineering.
The copyable move is smaller than the company
Few founders can copy a decade of healthcare data agreements or finance a map with tens of millions of dollars. They can copy Komodo's sequence. Start with one recurring, expensive decision. Build the minimum governed data foundation needed to answer it. Deliver the answer inside the user's workflow. Preserve the method so it can be inspected and rerun. Then watch what customers repeatedly ask next.
Aperture was a good wedge because it replaced a specific manual habit and introduced a surprising signal: recent patient care. The broader platform emerged after that proof. When users later underused the Map, Komodo did not merely add more data. It added guided products. When AI arrived, it did not abandon governance. It made auditability part of the sales argument.
The company has had its own reminder that good infrastructure does not suspend market gravity. Komodo reportedly prepared for a 2022 IPO after reaching a $3.3 billion valuation and roughly $150 million in annual recurring revenue. The listing did not happen. In December 2022, it cut about 9 percent of staff and closed a roughly $200 million structured equity infusion led by Coatue and Dragoneer. The founders called the restructuring a response to an uncertain economy. Private-company revenue and profitability today are not disclosed.
Since then, Komodo has widened distribution through Snowflake and AWS marketplaces, won Databricks' 2025 healthcare partner award, and moved Marmot from launch into enterprise deployments. The arc is less “AI startup appears” than “data company finally gets a conversational front door.” Its test will be whether buyers keep paying for the whole building behind that door.
The chatbot is the visible trick. The decade of cleaning, linking and governing data is the act.
Keep exploring the map
Komodo maintains product pages, customer examples and a video channel with interviews and platform explainers. Product access is sales-led; the company offers demos rather than public self-serve signup or published pricing.